The Epley Maneuver: How to Do It at Home for BPPV Vertigo
Updated October 2026
If the room spins for a few seconds every time you roll over in bed, look up, or bend down, the most likely cause is benign paroxysmal positional vertigo (BPPV). The Epley maneuver is a sequence of head and body positions that moves the loose inner-ear crystals behind BPPV back to where they no longer cause dizziness. Clinical guidelines recommend it as a first-line treatment for the most common form of BPPV.
This guide walks you through each step, explains how to tell which ear is affected, and covers who should not try the maneuver at home. If you’d rather have it done for you, our vestibular physiotherapy team in Guelph can confirm the diagnosis and perform the maneuver in the clinic.

What Is the Epley Maneuver?
The Epley maneuver is a canalith repositioning procedure. It was described by American ear, nose and throat surgeon Dr. John Epley, who published it in 1992. It treats BPPV by using gravity to guide small calcium carbonate crystals (otoconia) out of one of the inner ear’s balance canals and back into the part of the ear where they belong.
Your inner ear has three fluid-filled semicircular canals on each side that sense head rotation. In BPPV, crystals that have come loose drift into one of these canals. When you move your head into certain positions, the crystals shift, the fluid moves with them, and your brain receives a false signal that you are spinning. That is why BPPV vertigo is brief (usually less than a minute) and triggered by position changes rather than constant. You can read more about the condition in our guide to BPPV symptoms, causes and treatment.
Which type of vertigo does it treat?
The Epley maneuver is designed for posterior canal BPPV, which is the most common form. It is not the right treatment for:
- Horizontal (lateral) canal BPPV, which is treated with different repositioning maneuvers.
- Vestibular neuritis or labyrinthitis, where inflammation of the inner ear or balance nerve causes vertigo lasting hours to days.
- Ménière’s disease, which usually comes with hearing changes, ear fullness and ringing.
- Vestibular migraine, dizziness after a concussion, or dizziness from the neck.
This is why a proper assessment matters. If the Epley maneuver hasn’t worked for you, the most common reason is that the problem isn’t posterior canal BPPV, or it is in the other ear.

Before You Start: Is It BPPV, and Which Ear?
BPPV typically causes short spells of spinning vertigo when you lie down, roll over in bed, look up to a high shelf, or bend forward. Between spells you may feel slightly off-balance or queasy, but you should not have constant spinning, hearing loss, or neurological symptoms.
The Epley maneuver has to be done toward the affected ear. Clinicians identify it with a positional test called the Dix-Hallpike test: you sit on a bed, turn your head 45 degrees to one side, and lie back quickly so your head is slightly lower than your shoulders. If that side is affected, it brings on vertigo along with a characteristic flicking eye movement (nystagmus) that the examiner can see. The side that triggers your vertigo when lying back is usually the side to treat.
If you aren’t sure which ear is involved, don’t guess. Doing the maneuver toward the wrong side won’t fix the problem. A vestibular physiotherapist can check both sides, and test the horizontal canals with a roll test, in a single visit.
Who should not do the Epley maneuver at home
The maneuver involves lying back quickly with your head turned and tipped back, then rolling. Speak to your doctor or physiotherapist before trying it on your own if you have:
- Neck or back problems that limit movement, or recent neck or back surgery
- Known narrowing or disease of the arteries in your neck
- A history of retinal detachment or recent eye surgery
- An unstable heart condition
- Limited mobility or a high risk of falls, unless someone is there to help
- Dizziness that has never been assessed by a health professional
How to Do the Epley Maneuver: Step by Step
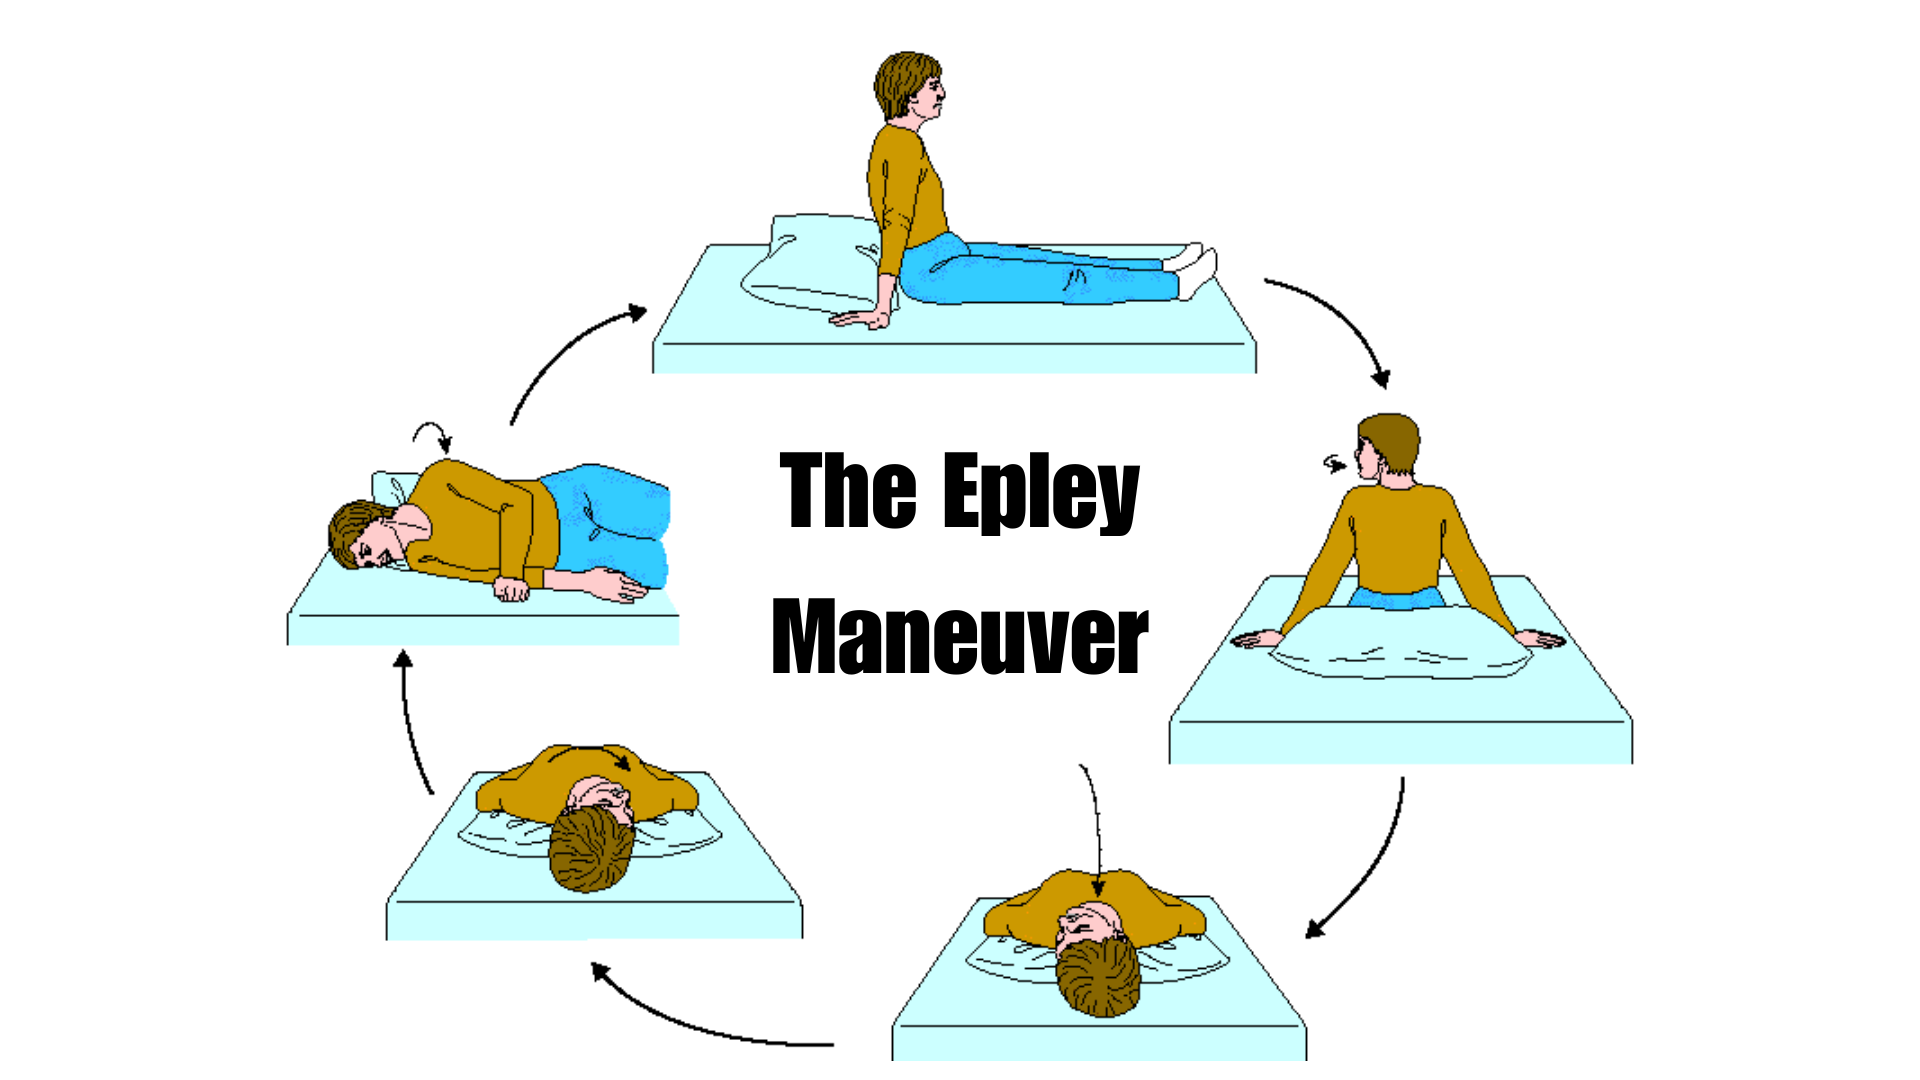
The steps below are for the right ear. For the left ear, follow the same steps with every head turn mirrored. Set up on a bed with a pillow placed so that, when you lie back, it will sit under your shoulders rather than your head. Having another person with you is a good idea, especially the first time.
- Sit upright on the bed with your legs out in front of you. Turn your head 45 degrees to the right (toward the affected ear).
- Lie back quickly with your head still turned to the right, so your shoulders land on the pillow and your head tips slightly back below shoulder level. This position usually brings on vertigo. Hold for 30 seconds, or until the spinning has stopped, whichever is longer.
- Turn your head 90 degrees to the left without lifting it, so you are now looking 45 degrees to the left. Hold for 30 seconds.
- Roll onto your left side, turning your head further so your nose points down toward the bed at about 45 degrees. Hold for 30 seconds.
- Sit up slowly on the left side of the bed, keeping your chin slightly tucked. Stay seated for a few minutes before you stand.
| Step | Position (right ear) | Hold |
|---|---|---|
| 1 | Sitting, head turned 45° right | Set-up |
| 2 | Lying back, head turned right and tipped slightly back | 30 sec or until vertigo stops |
| 3 | Lying back, head turned 45° left | 30 sec |
| 4 | On left side, nose pointing down at 45° | 30 sec |
| 5 | Sit up slowly on the left side | A few minutes |
Feeling dizzy during steps 2 to 4 is expected. It means the crystals are moving. Keep your eyes open if you can, and breathe slowly through it. Stop and seek help if you develop symptoms that feel different from your usual vertigo.
How often to repeat it
Home programs commonly repeat the sequence up to three times a day until you have gone 24 hours without positional vertigo. Follow the frequency your physiotherapist or doctor gives you. In clinical studies many people improve after one or two treatments, but some need several sessions, and BPPV can come back months or years later.
What to Expect After the Maneuver
It is normal to feel mildly lightheaded, unsteady or nauseated for a short time afterwards. Move carefully for the rest of the day, take your time getting out of bed, and avoid driving or heights until you feel steady.
You may have read that you need to sleep sitting upright or keep your head still for 24 to 48 hours. The current U.S. clinical practice guideline for BPPV recommends against routine post-maneuver restrictions, because studies haven’t shown they make a meaningful difference. If your physiotherapist has given you specific instructions, follow those.
If your vertigo improves but you still feel off-balance, that is common after BPPV, particularly in older adults. Targeted balance exercises can help. Our geriatric physiotherapy and vestibular programs focus on reducing fall risk.
When to See a Vestibular Physiotherapist
Book an assessment if:
- You aren’t sure your dizziness is BPPV, or which ear is affected
- You’ve tried the Epley maneuver a few times without improvement
- Your vertigo changes in character, for example it now happens when rolling side to side rather than lying back
- Your BPPV keeps coming back
- You feel unsteady on your feet or have had a fall
At Westwood Physiotherapy, our team includes physiotherapists certified in vestibular and oculomotor rehabilitation. An assessment includes positional testing to identify which canal and side are involved, the right repositioning maneuver for your type of BPPV, and a home program if you need one. Vestibular care is available at our Woodlawn Rd clinic in Guelph (Westwood Neuro and Vestibular Rehab), as well as at our Willow Rd and Tavistock locations. In Ontario you don’t need a doctor’s referral to see a physiotherapist.
When to get emergency care instead
BPPV does not cause neurological symptoms. Call 911 or go to the nearest emergency department if your dizziness is constant rather than brought on by position changes, or if it comes with any of the following:
- A sudden, severe headache
- Double vision or loss of vision
- Slurred speech, trouble swallowing, or facial drooping
- Weakness, numbness or tingling in your face, arm or leg
- Difficulty walking or loss of coordination
- Sudden hearing loss
- Fainting or chest pain
Frequently Asked Questions
Can I do the Epley maneuver on myself?
Yes. Many people with confirmed posterior canal BPPV learn to do the Epley maneuver at home. It works best once a clinician has confirmed which ear is affected, and it isn’t suitable for everyone, so check with a health professional first if you have neck, back, eye, heart or circulation problems.
How do I know which ear to treat?
The affected side is the one that brings on vertigo when you lie back quickly with your head turned toward it, which is the basis of the Dix-Hallpike test. If you can’t tell, a vestibular physiotherapist can test both sides in one visit.
How quickly does the Epley maneuver work?
Some people feel better after a single treatment. Others need it repeated over several days or sessions. If you’ve had no improvement after a few attempts, get reassessed, because you may have a different type of BPPV or a different cause of dizziness.
Is it normal to feel dizzy during the maneuver?
Yes. Brief vertigo in the lying-back position is expected and usually settles within a minute. Mild unsteadiness or nausea for a while afterwards is also common.
Do I need to sleep upright after the Epley maneuver?
Current clinical guidelines don’t recommend routine sleep or movement restrictions after the maneuver. Follow any specific advice your physiotherapist gives you, and get up slowly in the morning.
Does the Epley maneuver work for all types of vertigo?
No. It is designed for posterior canal BPPV. Vertigo from vestibular neuritis, Ménière’s disease, vestibular migraine or a concussion needs a different approach, which is why an assessment is worthwhile.
Get Help With Vertigo in Guelph and Tavistock
If vertigo is getting in the way of your day, our physiotherapists can confirm what is causing it and treat it. Contact Westwood Physiotherapy to book a vestibular assessment at our Woodlawn Rd, Willow Rd or Tavistock clinic.
References
- Bhattacharyya N, Gubbels SP, Schwartz SR, et al. Clinical Practice Guideline: Benign Paroxysmal Positional Vertigo (Update). Otolaryngology–Head and Neck Surgery. 2017;156(3_suppl):S1–S47. doi:10.1177/0194599816689667
- Hilton MP, Pinder DK. The Epley (canalith repositioning) manoeuvre for benign paroxysmal positional vertigo. Cochrane Database of Systematic Reviews. 2014;(12):CD003162. doi:10.1002/14651858.CD003162.pub3
- Epley JM. The canalith repositioning procedure: for treatment of benign paroxysmal positional vertigo. Otolaryngology–Head and Neck Surgery. 1992;107(3):399–404.
This article is general information and isn’t a substitute for an assessment by a qualified health professional.